Atrial Fibrillation and Stroke: When an Irregular Heartbeat Threatens the Brain
The heart beats irregularly, sometimes too fast, sometimes as if skipping a beat. Many describe this as a fluttering sensation in the chest. Yet, many feel nothing at all. This is precisely why atrial fibrillation is dangerous: it is the most common heart rhythm disorder and, at the same time, one of the strongest individual risk factors for stroke. The good news is that once detected, the risk can be drastically reduced.

What is Atrial Fibrillation
In atrial fibrillation, the upper chambers of the heart, the atria, do not beat in a coordinated manner but instead quiver. As a result, the heart does not pump blood effectively, allowing blood to pool in the left atrium, particularly in a small pouch-like structure called the left atrial appendage. This is where a blood clot forms.
The most common causes and triggers include high blood pressure, coronary artery disease, heart valve disease, heart failure, diabetes, obesity, sleep apnea, excessive alcohol consumption, and an overactive thyroid gland. The risk increases with age.
Symptoms to Recognize
A sensation of a racing or fluttering heart (palpitations), shortness of breath, fatigue, dizziness, reduced exercise tolerance, and sometimes chest discomfort.
When There Are No Symptoms
A large number of people do not experience any symptoms. In such individuals, atrial fibrillation is sometimes discovered only during a routine examination or, unfortunately, after a stroke has occurred. If you are over 65 or have high blood pressure, check your pulse at your wrist occasionally to see if the rhythm is regular. Smartwatches with an ECG function can point to a potential problem, but they do not provide a diagnosis. The findings must always be verified by a physician, as fibrillation can occur in episodes, meaning a single normal ECG does not rule out the presence of the arrhythmia.
Why Fibrillation Leads to Stroke
When blood pools in the atrium, a clot forms. If this clot breaks loose and enters the bloodstream, it can block an artery in the brain and cause an ischemic stroke.
The statistics are clear. Even when taking other risk factors into account, atrial fibrillation carries approximately a fivefold higher risk of ischemic stroke, and it is estimated to be the cause of roughly one in seven strokes.
Strokes Caused by Fibrillation Are More Severe
This is rarely mentioned, yet it is crucial. A blood clot originating from the heart is typically larger than one that forms directly within a brain artery, meaning it often blocks a major blood vessel. Consequently, these strokes result in more severe consequences, higher levels of disability, and higher mortality rates compared to strokes of other origins.
The Connection to Brain Bleeding
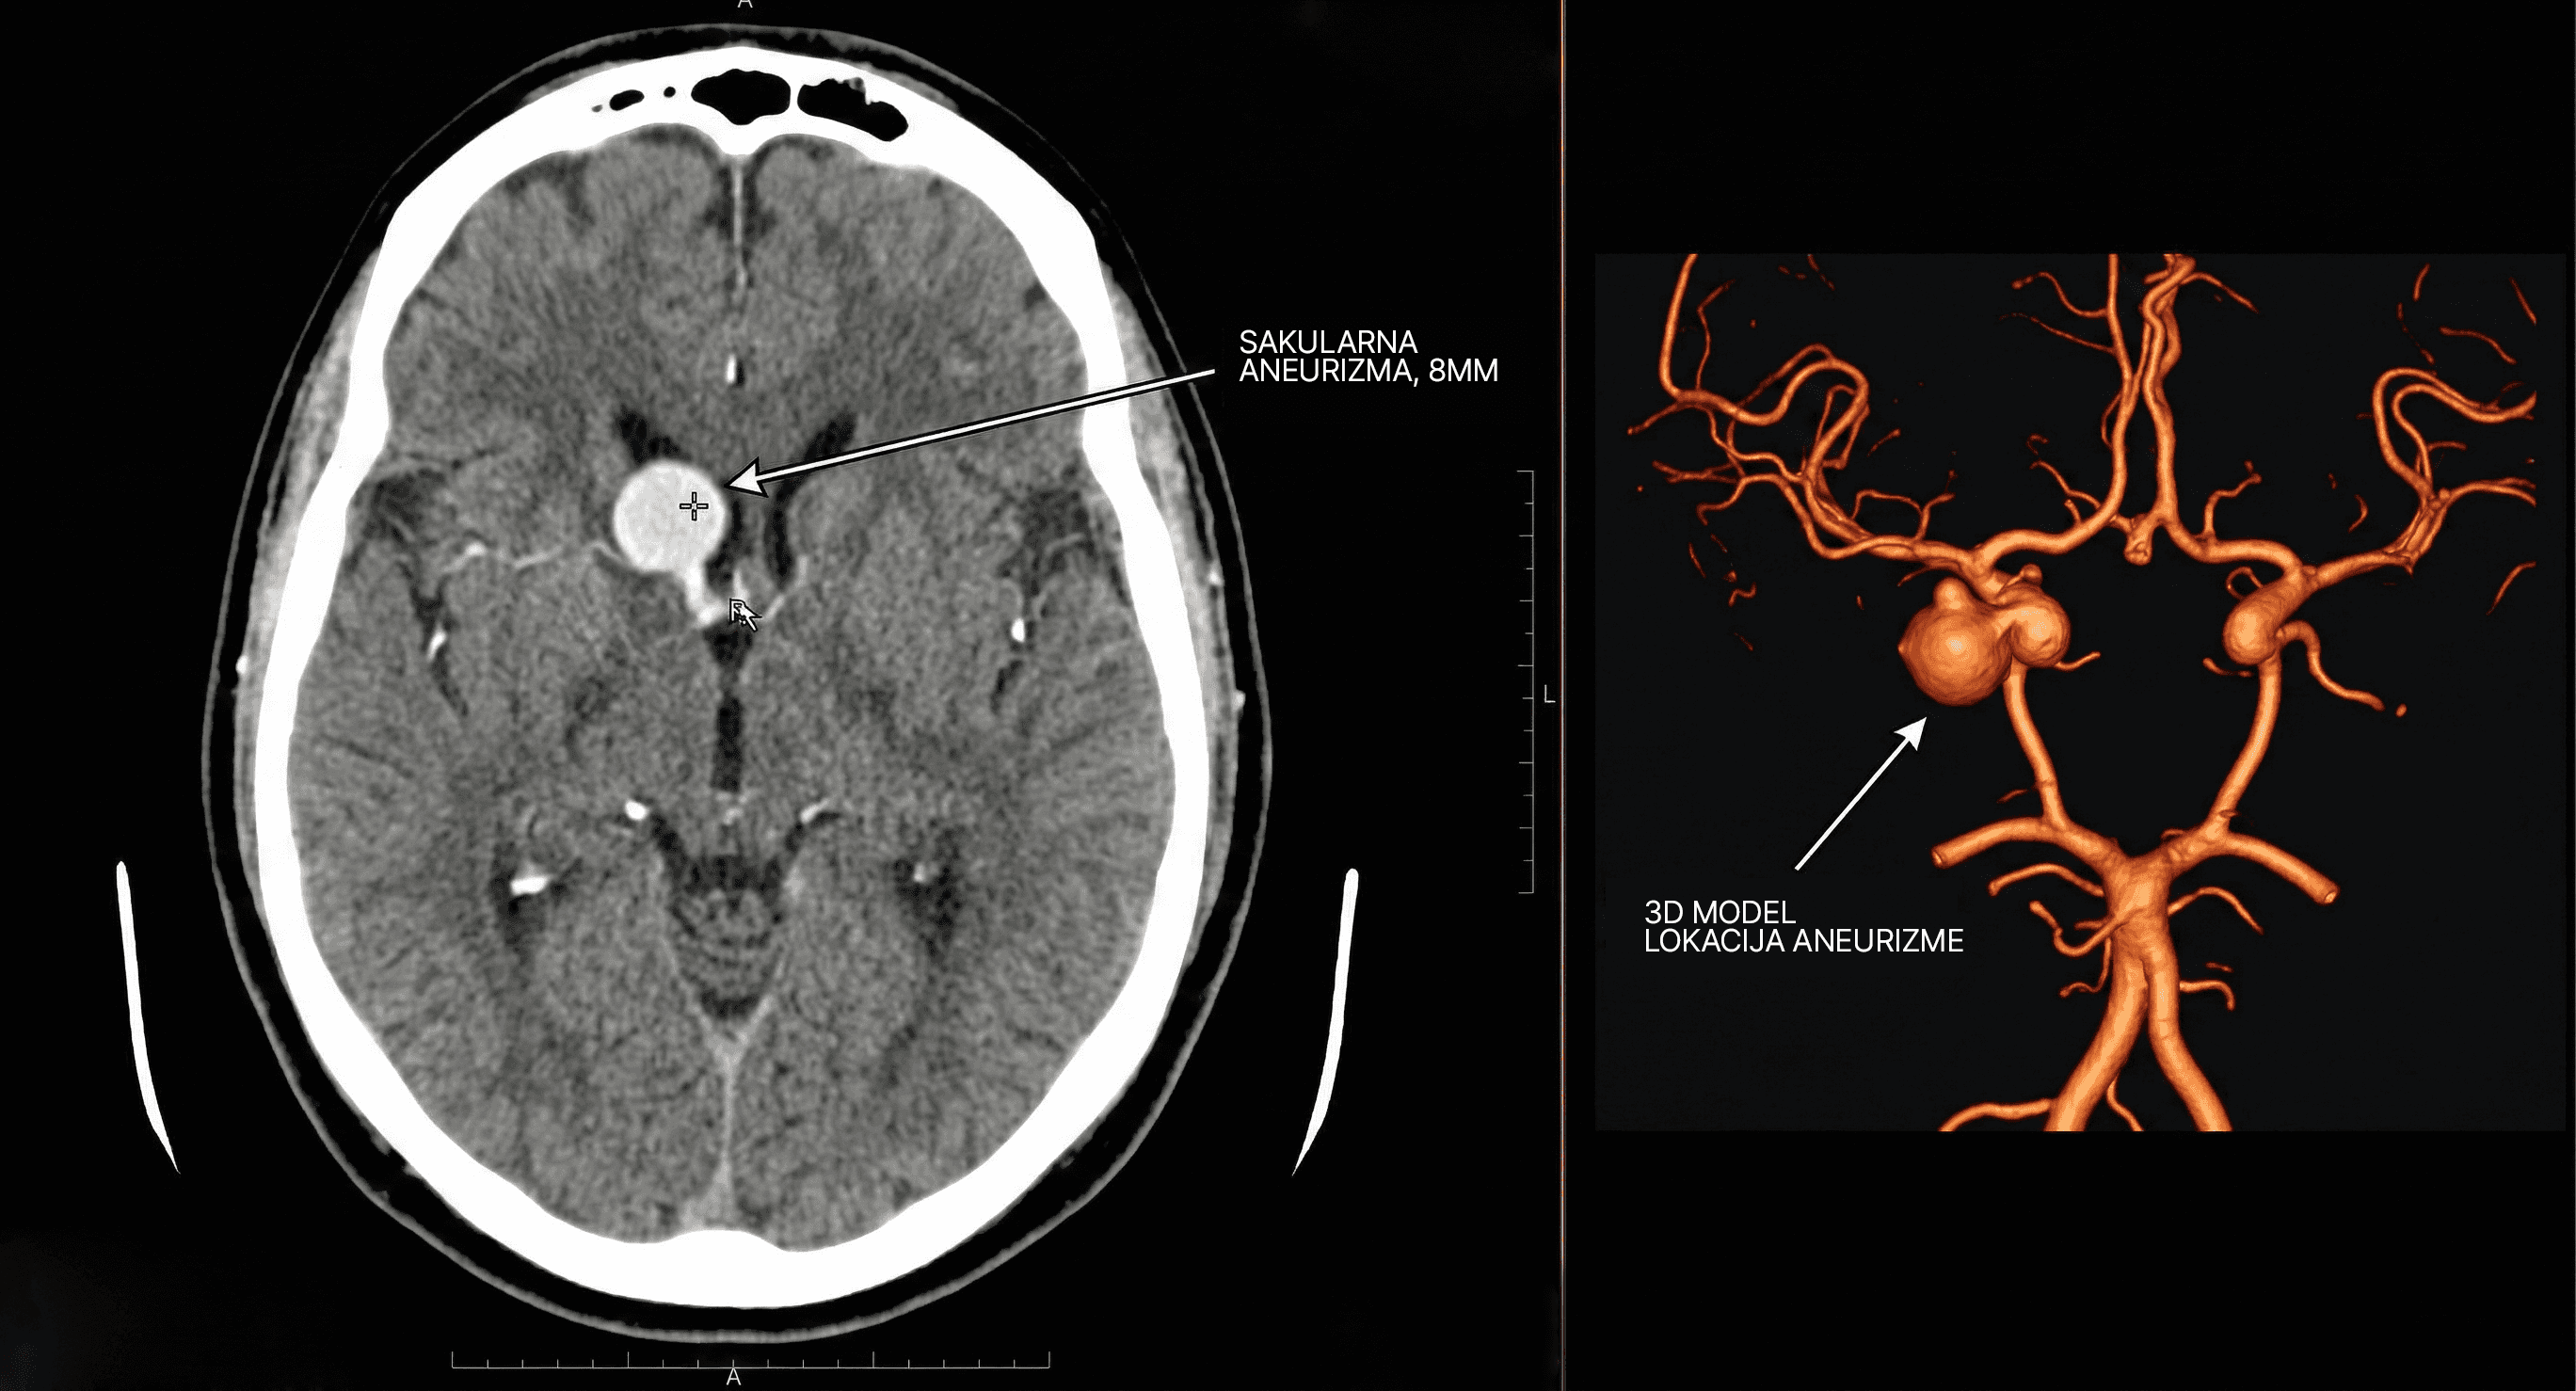
Atrial fibrillation does not cause hemorrhagic stroke. Hemorrhagic stroke occurs due to the rupture of a blood vessel, most commonly caused by long-term, uncontrolled high blood pressure. The only connection lies in the treatment: blood-thinning medications reduce the risk of clotting, but they increase the risk of bleeding. Therefore, a physician must carefully weigh these two risks for each individual patient.


How to Recognize a Stroke in Time
If a person with atrial fibrillation experiences a stroke, every minute is decisive for the outcome. Remember these four warning signs:
Face. Ask the person to smile. Does one side of their face droop?
Arms. Can they raise both arms and keep them up?
Speech. Is their speech clear, and do they understand what you are saying?
Time. If any of these signs are present, call emergency services immediately and note the exact time the symptoms began.
Other symptoms may include sudden loss of vision in one eye, severe dizziness, loss of balance, or the most intense headache of one's life. Do not wait for symptoms to subside on their own, and do not drive yourself to the hospital. Every passing minute results in the loss of vital brain cells.
How to Reduce the Risk
Blood-Thinning Therapy
This is the most critical preventive measure. For patients at elevated risk, a physician will prescribe oral anticoagulants. This risk is assessed using a scoring system that accounts for age, biological sex, blood pressure, diabetes, heart failure, and previous strokes.
Two points are of paramount importance here. First, aspirin is not a substitute for anticoagulant therapy; clinical guidelines explicitly advise against using antiplatelet drugs alone for stroke prevention in cases of atrial fibrillation. Second, treatment must never be discontinued voluntarily, even if you feel perfectly well, as the periods of highest risk are precisely those days when you believe the medication is unnecessary.
Heart Rate and Rhythm Control
A physician may prescribe medications to slow down or restore a normal heart rhythm. For some patients, catheter ablation is performed—a procedure designed to eliminate the areas of tissue causing the arrhythmia. It is vital to understand that a successful ablation does not automatically mean blood-thinning therapy can be stopped; in patients at elevated risk, guidelines recommend continuing anticoagulants regardless of the procedure's outcome.
Left Atrial Appendage Occlusion
For patients who cannot take anticoagulants due to a high risk of bleeding, a procedure is available to seal off the specific part of the atrium where blood clots most commonly form. This intervention is determined by a cardiologist.
Lifestyle Adjustments
Keeping blood pressure under control is the single most important lifestyle factor. Additionally, managing body weight, treating sleep apnea, engaging in regular physical activity, quitting smoking, and controlling blood sugar and cholesterol levels are essential. Alcohol requires special caution, as it directly triggers episodes of atrial fibrillation. European clinical guidelines recommend limiting consumption to a maximum of three standard drinks per week.

Frequently Asked Questions
Does atrial fibrillation always lead to a stroke?
No. While the risk is increased, it can be significantly reduced with appropriate therapy. Therefore, early detection is crucial.
I have atrial fibrillation but feel well. Do I need therapy?
The absence of symptoms does not mean the absence of risk. A blood clot can form even in a person who has no symptoms. The decision is made by a doctor based on a risk assessment, not on how you feel.
Is it enough to take aspirin?
No. Aspirin is not recommended as a substitute for anticoagulant therapy in atrial fibrillation.
Can a smartwatch detect atrial fibrillation?
It can indicate an irregular heart rhythm, which is a useful signal, but the diagnosis must be made by a doctor based on an ECG reading.
What if the episodes only occur occasionally?
Even occasional, paroxysmal atrial fibrillation carries a risk of stroke. The decision regarding therapy does not depend on how frequently the episodes occur.
In Conclusion
Atrial fibrillation is a common and treatable disorder, but if left unrecognized, it can be life-threatening. If you notice an irregular pulse, if you are over 65 years old, or if you have high blood pressure, consult your doctor and request an ECG. This is an examination that takes only a few minutes, but it can prevent a life-altering event.
This text is for informational purposes only and is not a substitute for a medical examination. For emergencies, please call your local emergency services.
Sources
Centers for Disease Control and Prevention. About Atrial Fibrillation. https://www.cdc.gov/heart-disease/about/atrial-fibrillation.html
European Society of Cardiology. 2024 ESC Guidelines for the Management of Atrial Fibrillation (overview of key recommendations, American College of Cardiology). https://www.acc.org/latest-in-cardiology/ten-points-to-remember/2024/09/17/04/05/2024-esc-guidelines-for-af-esc-2024
American College of Cardiology / American Heart Association. Management of Atrial Fibrillation: Guidelines (review in American Family Physician, 2025). https://www.aafp.org/pubs/afp/issues/2025/0200/practice-guidelines-atrial-fibrillation.html
Anticoagulation for Stroke Prevention in Patients with Atrial Fibrillation: A Review of the Literature and Current Guidelines. PubMed Central. https://pmc.ncbi.nlm.nih.gov/articles/PMC12230829/